
Temple Hair Transplant in Navi Mumbai: Grafts & Cost
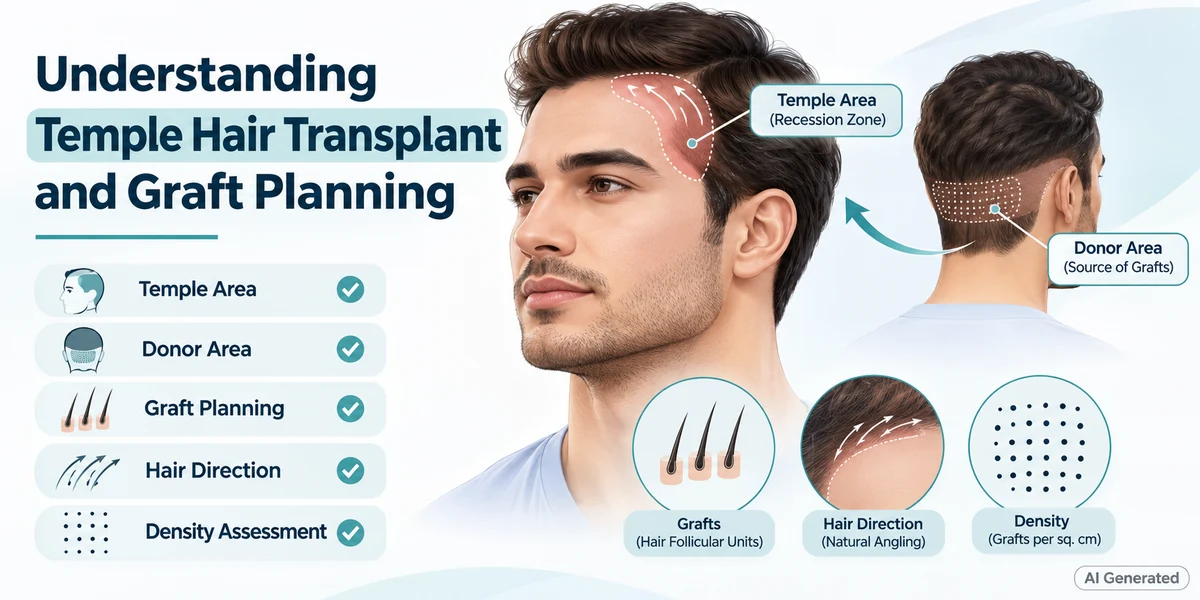
Temple Hair Transplant: Graft Planning, Procedure, Risks and Recovery
A temple hair transplant is a surgical procedure that transfers hair follicles from a donor area, usually the back or sides of the scalp, to selected areas of temple recession. It may be considered when hair loss has reduced the hair-bearing regions near the front and sides of the scalp.
Temple transplantation requires careful planning because hair in these regions often grows at shallow angles and follows distinctive directions.
The number of grafts required depends on the area being treated, existing hair density, hair calibre, available donor follicles and possible future hair loss.
A temple hair transplant does not stop progressive pattern baldness, and a natural-looking appearance cannot be guaranteed.
This educational guide explains the causes of temple recession, transplant planning, FUE and FUT techniques, graft requirements, complications, recovery and long-term considerations.
What Is a Temple Hair Transplant?
A temple hair transplant involves relocating follicular units to selected areas of hair loss near the sides of the frontal hairline.
The term temple region may refer to two related but different areas:
Frontotemporal recession: Thinning or hair loss near the corners of the frontal hairline.
Temporal points: The hair-bearing projections along the sides of the forehead that connect with the side hair.
These regions have different natural shapes and hair-growth patterns.
The distinction matters because restoring frontal corners is not identical to reconstructing temporal points.
A surgical plan must identify the precise anatomical area being treated.
Why Does Hair Recede at the Temples?
Several conditions can affect temple hair.
1. Androgenetic Alopecia
Androgenetic alopecia, also called pattern hair loss, commonly causes gradual recession of the frontal hairline and temples.
Genetic factors and sensitivity to androgens influence the process.
2. Age-Related Hairline Changes
Some individuals develop a more mature frontal hairline as they age.
Not every change in the temple area represents a condition requiring surgical treatment.
3. Traction Alopecia
Repeated tension from tight hairstyles can damage follicles, particularly around the hairline and temples.
Early cases may improve when traction is stopped, while prolonged damage can cause permanent scarring.
4. Scarring Alopecia
Certain inflammatory scalp diseases can damage follicles permanently.
Transplantation should not be undertaken without considering whether the disease is active.
5. Previous Surgery or Injury
Scarring from trauma or surgery can produce localised temple hair loss.
6. Other Hair-Loss Conditions
Diffuse shedding, alopecia areata and certain medical conditions may affect the temples.
Because treatments differ, the underlying diagnosis should be established before planning transplantation.
Why Are Temple Points Important in Hairline Design?
Temple points influence the transition between the frontal hairline and the side hair.
Their position and direction can affect how the forehead appears from the front, side and three-quarter views.
However, there is no universally ideal temple-point shape.
Natural variations depend on:
Age
Facial anatomy
Existing hairline
Hair characteristics
Pattern of recession
Sex-related and individual differences
Future hair-loss progression
Reconstructing the temples too aggressively may create an unnatural appearance if adjacent hair continues thinning.
Temple Recession vs Temporal Point Loss
| Feature | Frontotemporal recession | Temporal point loss |
|---|---|---|
| Main location | Corners of frontal hairline | Side projections near forehead |
| Typical appearance | Receding frontal corners | Reduced side hairline projection |
| Growth direction | Connects with frontal scalp | Often very shallow and side-directed |
| Main planning concern | Hairline position and future recession | Fine graft selection and precise angulation |
| Donor considerations | Adequate supply for frontal restoration | Suitable hair characteristics and limited donor supply |
A person may have one pattern, both patterns or neither.
Treatment planning should not assume they are the same.
Who May Be Suitable for a Temple Hair Transplant?
Temple transplantation may be considered in selected adults when the cause of hair loss is understood and donor follicles are suitable.
Important factors include:
Confirmed hair-loss diagnosis
Reasonably stable or predictable hair-loss pattern
Adequate donor density
Appropriate medical health
Suitable recipient scalp
Realistic expectations
Understanding of surgical scars
Acceptance of possible graft failure
Long-term planning for future thinning
A person with minimal recession may reasonably choose observation rather than surgery.
Who May Not Be Suitable?
Transplantation may be inappropriate or require postponement when:
Hair loss is rapidly progressing
The cause of temple thinning is uncertain
Active inflammatory scalp disease is present
Donor density is insufficient
Significant donor miniaturisation is present
The proposed design would consume excessive grafts
Medical conditions increase surgical risk
The patient expects guaranteed density or symmetry
Future hair loss has not been adequately considered
In some individuals, medical management or observation may be more appropriate.
How Is Temple Hair Transplant Planning Performed?
A temple transplant requires more than simply filling a visibly thin region.
Step 1: Confirm the Diagnosis
The surgeon or dermatologist identifies the reason for temple recession and considers whether transplantation is appropriate.
Step 2: Assess Existing Hair
Hairline position, temple-point anatomy, density and surrounding miniaturisation are reviewed.
Step 3: Evaluate Donor Hair
The back and sides of the scalp are assessed for follicular-unit density, hair calibre and stability.
Step 4: Review Future Hair Loss
Age, family history and current hair-loss patterns may help guide conservative planning.
Step 5: Mark the Proposed Design
The proposed temple region is marked so the patient can understand the planned position.
Step 6: Select Suitable Grafts
Appropriate follicular units are selected for the planned areas.
Finer single-hair units are commonly important near delicate temple borders.
Step 7: Plan Direction and Angle
Recipient-site orientation is planned to resemble nearby hair growth.
Step 8: Discuss Risks and Alternatives
Complications, recovery, long-term limitations and nonsurgical options should be explained before informed consent.
How Many Grafts Are Needed for a Temple Hair Transplant?
There is no standard graft number suitable for everyone undergoing temple restoration.
The amount depends on the size and location of the treatment area, existing density, hair characteristics and available donor follicles.
Important considerations include:
One-sided or bilateral recession
Size of the recipient area
Existing follicular density
Hair-shaft calibre
Number of hairs per follicular unit
Desired graft distribution
Donor supply
Potential future recession
A fixed graft range based only on mild, moderate or severe recession may be misleading.
Illustrative Graft Calculation
Suppose a proposed treatment area measures 20 cm² and the plan uses an average of 25 follicular units per cm².
The arithmetic estimate would be:
20 × 25 = 500 follicular units
This is only an illustrative calculation.
It does not establish a suitable graft density, safe donor availability or recommended treatment plan.
Clinical assessment is necessary before selecting a graft count.
Why Are Single-Hair Grafts Important in Temple Restoration?
A follicular unit may contain one or multiple hairs.
Temple hair frequently has a softer appearance than denser parts of the scalp.
Single-hair follicular units may therefore be selected for the leading border to avoid an abrupt appearance.
However, graft selection should also consider hair thickness, texture and the natural regional growth pattern.
Placing coarse multi-hair grafts at the edge can create visible clumps.
The goal is to match the surrounding anatomy, not to maximise the number of hairs in every graft.
Why Are Hair Angle and Direction Important?
The temple region is particularly sensitive to implantation angle.
Natural temple hairs can lie almost parallel to the skin surface.
Their direction may also change across the temporal point and adjacent hair-bearing regions.
If follicles are placed too upright, they may project outward.
This can make the transplanted hair difficult to style and visually conspicuous.
Incorrect direction may remain apparent even after the hair has grown for several months.
Suitable graft placement can reduce this risk but cannot guarantee a natural-looking result.
What Is the Difference Between FUE and FUT for Temple Restoration?
FUE and FUT are two methods for obtaining follicular units.
FUE — Follicular Unit Excision
FUE involves removing individual follicular units from the donor area using small punch instruments.
Each extraction heals with a small scar.
Excessive harvesting can cause visible donor thinning.
FUT — Follicular Unit Transplantation
FUT involves removing a strip of hair-bearing scalp and dissecting it into follicular units.
This produces a permanent linear donor scar.
FUE vs FUT Comparison
| Feature | FUE | FUT |
|---|---|---|
| Harvesting method | Individual follicular-unit extraction | Strip harvesting |
| Donor scars | Multiple small scars | Linear scar |
| Recipient-site planning | Requires precise placement | Requires precise placement |
| Temple angulation | Depends on recipient-site technique | Depends on recipient-site technique |
| Main donor concern | Overharvesting and patchiness | Linear scar and wound healing |
| Recovery | Individualised | Individualised |
Neither FUE nor FUT automatically produces better temple design.
The appearance depends on appropriate planning, graft selection, placement and healing.
How Is a Temple Hair Transplant Performed?
The exact technique varies, but a typical operation involves several stages.
1. Scalp and Hairline Assessment
The treatment area and donor zone are evaluated.
2. Surgical Planning
The temple shape and recipient-site directions are discussed.
3. Anaesthesia
Local anaesthesia is commonly used, sometimes with additional measures according to clinical requirements.
4. Donor Harvesting
Follicular units are obtained using the selected technique.
5. Graft Preparation
Grafts are inspected, prepared and maintained under appropriate conditions.
6. Recipient-Site Creation
Small sites are prepared in the temple region with attention to orientation and distribution.
7. Graft Placement
Follicular units are placed into the planned sites.
8. Postoperative Care
Instructions are provided for wound care, washing, medications, activity and follow-up.
The procedure must be undertaken by appropriately qualified professionals with suitable clinical supervision and safety arrangements.
Why Is Donor Area Preservation Important?
Donor hair is a limited resource.
Harvesting follicles for the temples reduces the number available for possible future procedures.
This matters because hair loss may continue in the frontal scalp, mid-scalp and crown.
An excessively dense or aggressively positioned temple design may consume grafts that could be needed later.
Donor assessment should include:
Follicular-unit density
Hair calibre
Miniaturisation
Donor-zone stability
Previous harvesting
Existing scars
Future hair-loss expectations
The objective is not necessarily to harvest the maximum possible number of grafts.
What Are the Risks of Temple Hair Transplantation?
Temple transplantation carries recognised surgical risks.
Bleeding and Infection
Bleeding, infection or poor wound healing may occur in donor or recipient areas.
Permanent Scarring
FUE and FUT produce permanent donor scars.
Recipient-area changes or scarring may also occur.
Poor Graft Survival
Not every transplanted follicle necessarily survives.
Incorrect Hair Direction
Grafts may grow at unnatural angles.
This is particularly important around temporal points.
Uneven Density
Differences in graft growth and placement can produce irregular coverage.
Shock Loss
Temporary shedding of nearby native hair may occur.
Recovery may be incomplete in some cases, particularly where follicles were already miniaturised.
Donor Overharvesting
Excessive extraction can create visible thinning or patchiness.
Sensory Changes
Temporary or persistent numbness or unusual scalp sensations may occur.
Unnatural Temple Shape
An overly pointed, low or prominent reconstruction may look inconsistent with surrounding hair.
Revision Surgery
Additional surgery may occasionally be considered, but correction is not always possible and further procedures carry risks.
Temple Hair Transplant Recovery Timeline
| Recovery stage | Common changes | General precautions |
|---|---|---|
| Days 1–3 | Redness, tenderness and possible swelling | Protect grafts and follow prescribed care |
| Days 4–7 | Small crusts and continued healing | Avoid scratching or rubbing |
| Weeks 1–2 | Crusts gradually loosen; redness may improve | Follow washing and activity instructions |
| Weeks 2–8 | Transplanted hair shafts may shed | Understand shedding does not necessarily indicate graft failure |
| Months 3–4 | Early regrowth may become visible | Growth may remain sparse and uneven |
| Months 4–6 | Further hair growth may occur | Continue appropriate follow-up |
| Months 6–9 | Coverage and hair characteristics may evolve | Assess progress cautiously |
| Months 9–12 | More mature growth may become apparent | Review remaining concerns |
| Months 12–18 | Further maturation may occur in some patients | Consider long-term hair-loss management |
These are general timelines, not guaranteed milestones.
Healing and growth differ between individuals.
Is Shedding Normal After a Temple Hair Transplant?
Some transplanted hair shafts may shed several weeks after surgery.
This can be part of the normal postoperative hair cycle.
The transplanted follicle may remain beneath the skin even when the visible shaft sheds.
However, not all grafts necessarily survive.
Persistent redness, scarring, pain or failure of expected growth should be evaluated medically.
How Long Does It Take to See Temple Hair Growth?
Early regrowth may become noticeable after several months.
Coverage often changes progressively during the following months.
However, hair growth is variable.
The final appearance depends on:
Follicular survival
Hair calibre
Graft distribution
Recipient scalp condition
Healing
Natural growth cycles
Ongoing loss of nearby native hair
A particular density, growth rate or cosmetic outcome cannot be guaranteed.
Are Temple Hair Transplant Results Permanent?
Transferred follicles may continue growing for many years when harvested from relatively stable donor regions.
However, this does not mean the surrounding hair is protected from future hair loss.
Progressive androgenetic alopecia can cause untreated native hairs to recede further.
This may create visible gaps around the transplanted temples.
Long-term medical management may therefore remain relevant.
The donor zone itself can also become thinner in some individuals.
Temple Hair Transplant vs PRP: What Is the Difference?
Platelet-rich plasma, or PRP, involves preparing a platelet-containing product from the patient’s blood and injecting it into selected scalp areas.
It differs from transplantation because it does not relocate follicles.
| Feature | Temple hair transplant | PRP |
|---|---|---|
| Treatment type | Surgical | Injection-based |
| Main action | Relocates follicles | Investigational or adjunctive treatment for selected hair-loss conditions |
| Donor grafts needed | Yes | No |
| Established bald areas | May be considered when suitable | Cannot reliably replace absent follicles |
| Risks | Scarring, infection, poor graft growth, donor depletion | Injection reactions, infection and uncertain benefit |
| Evidence | Established surgical approach for selected patients | Variable and limited for specific indications |
| Guaranteed regrowth | No | No |
PRP is not a universally established substitute for transplantation.
Its use as an adjunct should be evaluated individually because protocols and supporting evidence vary.
Can Temple Recession Be Treated Without Surgery?
Some people with early pattern hair loss may be considered for medical treatment.
Options may include topical minoxidil or prescription treatments such as finasteride for appropriately selected patients.
These treatments have different indications and possible adverse effects.
Medical therapy may help maintain existing hair or slow progression in some individuals, but regrowth is not guaranteed.
Other causes of temple hair loss, such as traction or inflammatory disease, require diagnosis-specific management.
A medical evaluation should occur before assuming surgery is necessary.
Normal Healing vs Warning Signs
| May occur during recovery | Requires medical assessment |
|---|---|
| Mild redness that gradually improves | Spreading redness or warmth |
| Temporary tenderness | Severe or worsening pain |
| Small crusts around grafts | Pus or significant discharge |
| Temporary swelling | Rapidly increasing swelling |
| Temporary hair shedding | Persistent inflammatory scalp symptoms |
| Gradual regrowth | Progressive scarring or concerning persistent changes |
| Mild donor-site discomfort | Significant bleeding or increasing donor-site pain |
Fever, significant bleeding, spreading infection or severe pain should be assessed promptly.
Temple Hair Transplant: Safety and Planning Checklist

Before undergoing transplantation:
Confirm the diagnosis: Identify the cause of temple recession.
Distinguish treatment areas: Understand whether frontal corners, temporal points or both are involved.
Assess future hair loss: Consider possible progression before finalising the design.
Review donor availability: Examine density, calibre and donor stability.
Discuss graft selection: Understand the role of suitable single-hair grafts.
Review implantation direction: Temple hairs require careful angle and orientation.
Avoid aggressive reconstruction: Understand the long-term consequences of an excessively low or prominent design.
Compare FUE and FUT: Review donor scars and technique-specific limitations.
Discuss complications: Include infection, graft failure, unnatural growth and donor overharvesting.
Consider alternatives: Medical treatment or no surgery may be reasonable.
Follow postoperative instructions: Protect both donor and recipient areas.
Recognise warning signs: Report fever, worsening pain or unusual discharge.
Plan long-term follow-up: Consider ongoing loss of surrounding hair.
This checklist supports informed decision-making but cannot eliminate surgical risks.
Before undergoing transplantation:
Confirm the diagnosis: Identify the cause of temple recession.
Distinguish treatment areas: Understand whether frontal corners, temporal points or both are involved.
Assess future hair loss: Consider possible progression before finalising the design.
Review donor availability: Examine density, calibre and donor stability.
Discuss graft selection: Understand the role of suitable single-hair grafts.
Review implantation direction: Temple hairs require careful angle and orientation.
Avoid aggressive reconstruction: Understand the long-term consequences of an excessively low or prominent design.
Compare FUE and FUT: Review donor scars and technique-specific limitations.
Discuss complications: Include infection, graft failure, unnatural growth and donor overharvesting.
Consider alternatives: Medical treatment or no surgery may be reasonable.
Follow postoperative instructions: Protect both donor and recipient areas.
Recognise warning signs: Report fever, worsening pain or unusual discharge.
Plan long-term follow-up: Consider ongoing loss of surrounding hair.
This checklist supports informed decision-making but cannot eliminate surgical risks.
Frequently Asked Questions
1. What is a temple hair transplant?
A temple hair transplant is a surgical procedure that transfers follicular units from a suitable donor region to selected areas of temple recession. It may involve the frontal corners, temporal points or both.
2. How many grafts are needed for a temple hair transplant?
There is no fixed graft number. Requirements depend on the size of the recipient area, existing density, hair calibre, donor availability and the planned hairline design.
3. Is FUE suitable for temple hair transplantation?
FUE may be used for selected temple transplants. However, natural-looking results depend on graft selection, recipient-site angles, hair direction and surgical planning rather than the harvesting method alone.
4. Why is temple hair transplant design difficult?
Temple hairs often grow at shallow angles and have distinctive directions and finer characteristics. Incorrect graft placement may produce an unnatural appearance even when transplanted follicles grow.
5. How long does recovery take after a temple hair transplant?
Initial healing often takes one to two weeks. Transplanted hair shafts may shed during the following weeks, while visible regrowth and maturation may continue over several months.
6. Are temple hair transplant results permanent?
Some transplanted follicles may continue growing long-term. However, native hair around the transplanted region can continue thinning, and no particular cosmetic appearance is guaranteed permanently.
7. What are the main risks of temple hair transplantation?
Possible complications include bleeding, infection, scarring, poor graft survival, temporary or persistent numbness, shock loss, unnatural hair direction, donor overharvesting and revision surgery.
Conclusion
Temple hair transplantation is a specialised form of hair restoration that requires careful assessment of the frontal hairline, temporal points and donor follicles.
Its planning differs from transplantation into larger scalp areas because temple hairs often have finer characteristics and unusually shallow growth angles.
The procedure may be considered for selected cases of permanent temple recession, but it does not stop progressive hair loss or guarantee natural-looking density.
Understanding anatomical differences, graft requirements, donor limitations, complications and long-term hair-loss management is essential before considering treatment.
Disclaimer: All content and visuals on this website are for educational and informational purposes only. Images may be AI-generated or illustrative. Individual treatment results may vary. This information does not replace professional medical advice, diagnosis or consultation.