
Epithelialisation in Wound Healing: How New Skin Forms
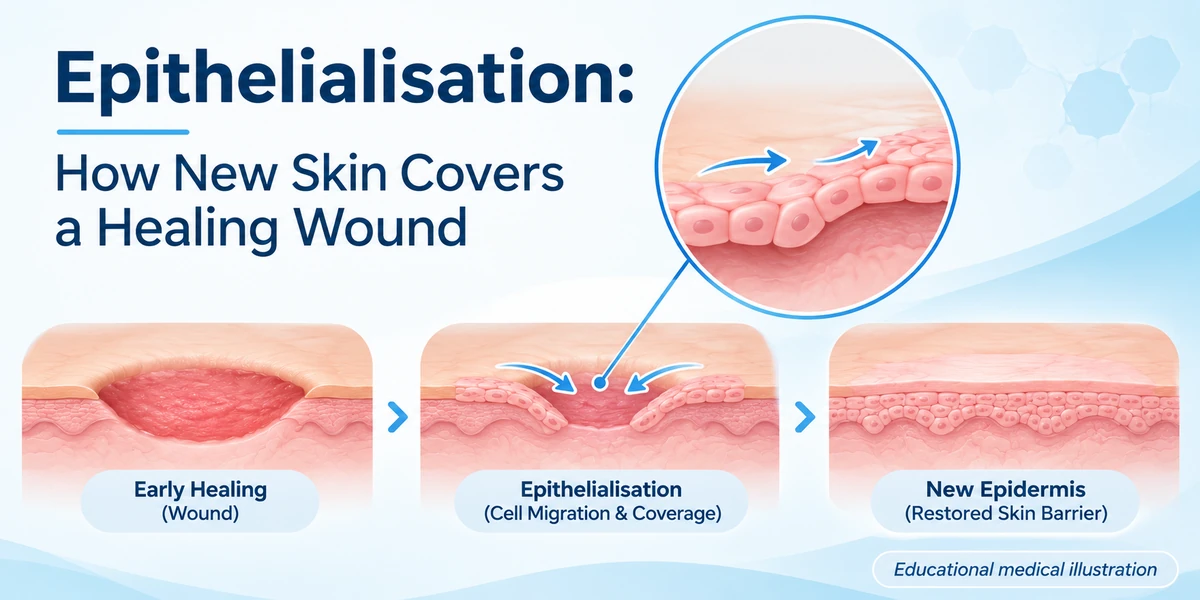
Epithelialisation is the process by which new skin cells migrate, multiply and differentiate to close a wound and rebuild the protective barrier. In the first few days after injury, basal keratinocytes at the wound edge become activated, slide across the provisional matrix, and proliferate until they meet in the centre of the defect. This rapid resurfacing limits fluid loss, reduces infection risk, and sets the stage for later remodeling of the scar. The speed and quality of epithelialisation depend on the wound environment, the health of the individual, and the presence of any complicating factors.
What Is Epithelialisation?
Epithelialisation, also called re‑epithelialisation, describes the resurfacing of a wound with new epithelium. It is a key phase of the proliferative stage of cutaneous wound healing, occurring after haemostasis and inflammation. The newly formed epidermal layer originates from basal keratinocytes that migrate from the wound margins and, in deeper wounds, from epidermal stem cells within hair follicles and sweat glands.
Why Does Epithelialisation Occur?
The primary purpose of epithelialisation is to re‑establish the skin’s barrier function. A continuous epidermis prevents dehydration, blocks external pathogens, and restores sensory function. The process is driven by a coordinated network of growth factors (e.g., EGF, FGF, TGF‑β), cytokines, and extracellular‑matrix cues that signal keratinocytes to detach, move, divide and differentiate.
Who May Be Affected?
All individuals who sustain a cut, abrasion, surgical incision or pressure ulcer undergo epithelialisation. However, people with compromised health—such as those with diabetes, peripheral vascular disease, or chronic malnutrition—often experience delayed or incomplete epithelialisation, increasing the risk of infection and chronic wounds.
How Does It Work?
Keratinocyte activation begins when inflammatory cells release cytokines (IL‑1, IL‑6, TNF‑α) and growth factors. These signals trigger the following steps:
- Migration: Basal keratinocytes loosen their attachments to the basement membrane, extend lamellipodia, and crawl across the wound bed. They use integrin receptors to bind provisional matrix proteins such as fibronectin and vitronectin.
- Proliferation: While moving, keratinocytes enter the cell cycle, doubling their numbers to cover the defect. Epidermal stem cells in the hair follicle bulge provide an additional source of proliferative cells, especially in deeper wounds.
- Differentiation: Once the migrating front meets in the centre, cells begin to stratify, forming the basal layer, spinous layer, granular layer and finally the cornified outer layer that restores barrier integrity.
Successful epithelialisation requires a moist, non‑infected wound environment that supports cell movement. Moisture maintains a hydrated matrix, reduces crust formation, and allows growth‑factor diffusion. This principle is highlighted in Lessons From Epithelialization: The Reason Behind Moist Wound Environment.
What Outcomes Are Realistic?
Healing timelines vary widely. Superficial partial‑thickness wounds may re‑epithelialise within 3–7 days, whereas full‑thickness wounds can take several weeks. Larger surface area, deeper depth, and locations with poorer blood supply (e.g., lower legs, sacral region) generally prolong the process. Individual factors such as age, nutritional status, and comorbidities also influence speed.
Benefits and Limitations
The main benefit of rapid epithelialisation is early barrier restoration, which lowers infection risk and improves cosmetic outcomes. However, if the wound environment is hostile—e.g., excessive exudate, high bacterial load, or persistent inflammation—keratinocyte migration can be stalled, leading to chronic non‑healing wounds. In such cases, adjunctive therapies (negative‑pressure wound therapy, bio‑engineered skin substitutes) may be considered, but they do not replace the fundamental need for a clean, well‑vascularised wound bed.
Risks or Possible Complications
Delayed epithelialisation can result in:
- Infection and cellulitis
- Excessive scar formation, including hypertrophic scars or keloids (see our keloid risk assessment)
- Persistent wound drainage or maceration if moisture balance is not maintained
- Chronic pain and reduced function
Systemic factors such as uncontrolled diabetes, smoking, or immunosuppression increase these risks.
Recovery and Follow‑Up Care
Optimal wound care supports epithelialisation by:
- Keeping the wound moist with appropriate dressings (hydrocolloid, silicone, or alginate) while avoiding excessive maceration.
- Controlling infection with timely debridement and, when indicated, topical or systemic antimicrobials.
- Ensuring adequate nutrition—especially protein, vitamin C, zinc, and vitamin A—which are essential for keratinocyte proliferation.
- Managing comorbidities (glycaemic control in diabetes, peripheral arterial disease) to improve perfusion.
Regular assessment by a healthcare professional is advised to monitor epithelial progress, detect early signs of infection, and adjust the dressing regimen as the wound contracts.

When to Seek Medical Advice
Contact a clinician promptly if you notice any of the following:
- Increasing pain, redness, warmth, or swelling around the wound.
- Purulent discharge or foul odour.
- Stalled healing after two weeks for a partial‑thickness wound or four weeks for a deeper wound.
- Signs of systemic infection (fever, chills).
- Underlying conditions that may impair healing (e.g., uncontrolled diabetes, peripheral vascular disease).
Medical References
Frequently Asked Questions
What triggers keratinocytes to start migrating during wound healing?
Inflammatory cells release cytokines such as IL-1 and growth factors like EGF, which signal basal keratinocytes to detach, extend lamellipodia and crawl across the provisional matrix.
How long does epithelialisation usually take for a superficial cut?
For a superficial partial-thickness wound, epithelial cells typically close the defect within 3 to 7 days, provided the wound remains moist and free of infection.
Can a moist dressing improve epithelialisation?
Yes, a moist environment maintains a hydrated matrix, reduces crust formation and enhances growth-factor diffusion, all of which accelerate keratinocyte migration.
Why do people with diabetes often experience delayed epithelialisation?
Diabetes impairs blood flow, reduces immune cell function and alters growth-factor signaling, which together slow keratinocyte proliferation and migration.
What are early warning signs that epithelialisation is not progressing?
Signs include persistent wound drainage, increasing pain or redness, lack of new epithelial tissue after two weeks (partial-thickness) or four weeks (deep wounds), and any discharge suggesting infection.
Is scar formation inevitable after epithelialisation?
A scar forms as part of normal remodeling, but the size and appearance depend on wound depth, tension, and individual factors; good epithelialisation can minimise excessive scarring.
Should I use over-the-counter creams to speed up epithelialisation?
Topical agents are only beneficial if they keep the wound moist and are free from irritants; unproven creams may delay healing or cause allergic reactions, so follow professional advice.
Conclusion
Epithelialisation is the body’s rapid response to restore the skin barrier after injury, relying on keratinocyte migration, proliferation and differentiation within a supportive wound environment. Understanding the cellular mechanisms, factors that delay healing, and evidence‑based wound‑care practices helps clinicians and patients promote timely closure while recognising when professional intervention is required.
Medical Disclaimer
This article is intended for general educational purposes only and does not replace individual medical advice, diagnosis or treatment. Suitability, risks and outcomes vary. Consult a qualified healthcare professional for medical guidance specific to your situation.