
5 Months After Hair Transplant No Density
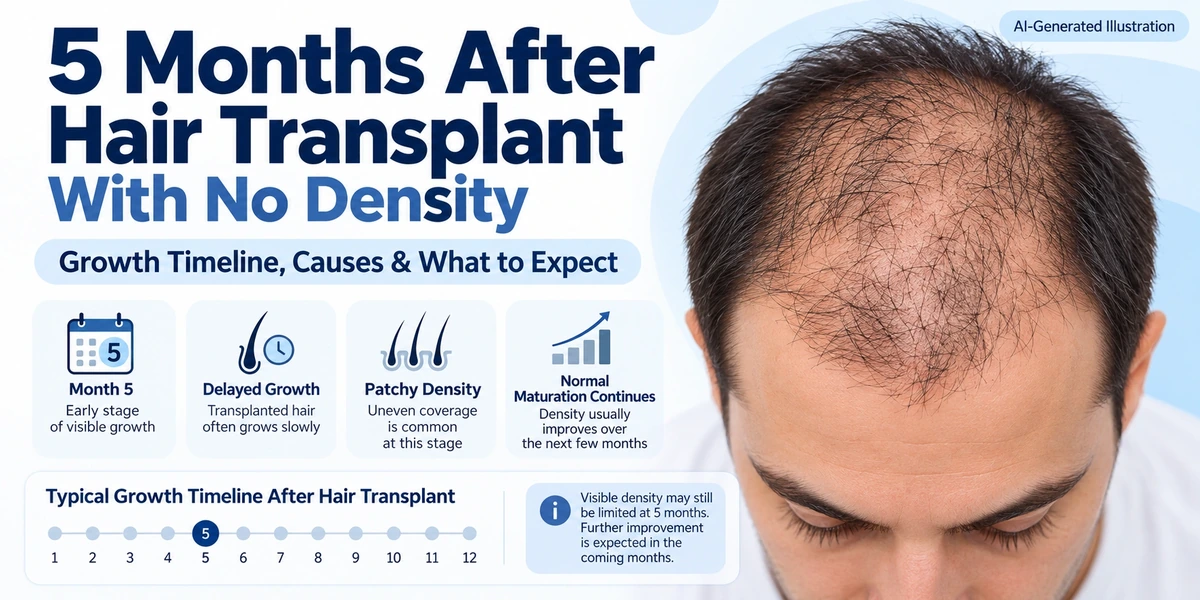
Hair transplantation involves moving healthy hair follicles from a donor area to regions of the scalp affected by hair loss. Although follicles are placed during surgery, visible hair growth and increased density take considerably longer to develop.
If you notice little or no hair density 5 months after a hair transplant, it is understandable to wonder whether the transplanted follicles are growing normally.
At this stage, some individuals begin noticing new hair growth, while others experience slower or uneven progress. Newly emerging hairs may initially appear thin, short or sparse, making overall density less noticeable.
Limited hair density at five months does not automatically indicate transplant failure. This article explains delayed growth, the first-year recovery timeline, possible causes of low density and when medical assessment may be necessary.
Is It Normal to Have No Hair Density 5 Months After a Hair Transplant?
Hair growth after transplantation varies between individuals. At approximately five months, some transplanted follicles may have started producing visible hair, while others may remain in an earlier stage of the growth cycle.
The American Academy of Dermatology’s guidance on hair transplant results explains that many patients notice results between six and nine months, while some need around twelve months.
Possible observations at five months include:
- Short, newly emerging hairs
- Uneven growth across the transplanted area
- Fine hair strands and visible scalp
- Gradual improvement in coverage
- Different growth rates at the hairline and crown
Little visible change at five months is not proof of a failed transplant. However, complete absence of new growth or concerning symptoms should be discussed with a qualified healthcare professional.
Understanding the Hair Transplant Growth Cycle
Hair follicles move through biological phases. The International Society of Hair Restoration Surgery’s guide to the hair growth cycle offers further educational background about follicular growth and pattern hair loss.
Anagen Phase: Active Growth
During anagen, the follicle produces a hair shaft that grows over time. Scalp follicles may remain in this phase for years.
Catagen Phase: Transition
Catagen is a brief transition during which active growth slows and the follicle changes structure.
Telogen Phase: Resting
In telogen, the follicle rests before returning to active growth. After transplantation, follicles may spend time in a resting phase before new hair becomes visible.
Exogen Phase: Shedding
Exogen describes the release of a hair shaft. Shedding of transplanted hair shafts does not necessarily mean the underlying follicles have been lost.
Hair Transplant Growth Timeline: Month by Month
| Time after surgery | Common observations |
|---|---|
| First 1–2 weeks | Scalp healing, temporary redness and crusting |
| Weeks 2–8 | Shedding of transplanted hair shafts may occur |
| Months 2–3 | The area may appear thinner while follicles rest |
| Months 3–4 | Early new growth may begin to appear |
| Month 5 | Fine, short and uneven growth may be visible |
| Months 6–9 | Coverage and visible density may improve |
| Months 9–12 | Additional growth, thickening and maturation |
| Months 12–18 | Further maturation may occur for some people |
These are general patterns, not fixed milestones or guaranteed outcomes. To understand the earlier shedding stage, see this related educational article on hair transplant recovery at six weeks.

First Month: Healing and Shedding

Small crusts, redness, tenderness or swelling can occur as the scalp heals. Some transplanted shafts remain visible temporarily and later shed. Follow the medical team’s wound-care instructions.
Months 2–3: Resting and Reduced Visible Density
The transplanted area may look thin because many shafts have shed before new visible hair has developed. Surface appearance alone does not establish whether follicles remain viable.
Months 4–5: Early Hair Emergence
New hairs may be fine, short or uneven. Some follicles produce visible strands earlier than others, so the area can still look sparse or patchy.
Months 6–9: Gradual Improvement
More hairs may become visible and existing strands may lengthen or thicken. The extent and speed of change differ between individuals.
Months 9–12 and Beyond: Maturation
Hair appearance may continue changing into the following months. Some individuals, particularly those with crown transplantation, experience further maturation beyond twelve months.
Why Is There Low Hair Density 5 Months After a Hair Transplant?
1. Post-Transplant Hair Shedding
Transplanted shafts can shed during the early recovery period. This temporary shedding does not always mean the follicle is damaged.
2. Delayed Follicular Growth
Follicles do not all resume visible hair production at once. Some remain in a resting stage longer than others.
3. Fine or Short Newly Growing Hair
Early strands may be too short or thin to provide significant coverage. Their visible appearance may change as they grow.
4. Donor Hair Characteristics
Hair-shaft thickness, texture, curl, colour and contrast with the scalp can influence perceived density, even when follicle counts are similar.
5. Graft Number and Distribution
Coverage depends partly on the number and distribution of viable follicles across the recipient area. Graft numbers alone do not determine the final appearance.
6. Continuing Loss of Existing Hair
Transplantation does not necessarily stop androgenetic alopecia in non-transplanted hair. For related background, read about the causes of male pattern hair loss and available treatment options.
7. Scalp or Medical Conditions
Inflammatory scalp disease, nutritional deficiencies, thyroid disorders or infection may complicate hair growth in some cases. Assessment depends on symptoms and clinical findings.
8. Reduced Graft Survival
Some follicles may not survive or produce expected growth because of tissue injury, infection, impaired blood supply or other factors. Low density at five months alone does not confirm poor graft survival.
Does No Density at 5 Months Mean the Hair Transplant Has Failed?
Not necessarily. Five months is usually an intermediate recovery stage. New hair may be short, fine or unevenly distributed. A meaningful evaluation considers new growth, scalp health, graft distribution, donor characteristics and ongoing natural hair loss.
Persistent absence of visible growth, worsening scalp symptoms or increasing hair loss warrants clinical review rather than reassurance based on time alone.
What Should You Do if There Is No Density After 5 Months?
Allow Time for Growth
Avoid treating five-month density as the final result. New strands may still be emerging and maturing.
Attend Follow-Up Assessments
A qualified healthcare professional can examine the scalp, donor region, new hair emergence and signs of inflammation.
Monitor Consistently
Personal progress photographs taken in similar lighting, angles and hair lengths may help document changes without presenting them as proof of guaranteed outcomes.
Follow Individual Scalp-Care Instructions
Use gentle hair care and follow postoperative recommendations. Avoid unnecessary rubbing, irritating products or self-directed changes to medication.
Discuss Ongoing Hair Loss
Where non-transplanted hair continues to thin, clinicians may assess whether management of the underlying hair-loss condition is appropriate.
Can Hair Density Improve After the Fifth Month?
Yes. Visible density can improve as more follicles produce hair, existing strands lengthen and some hairs become thicker. Changes in scalp redness and styling can also influence perceived coverage.
Nevertheless, improvement is not guaranteed. The final appearance depends on graft survival, pre-existing hair characteristics, the size of the transplanted area and continuing natural hair loss.
How Can You Support Healthy Hair Growth After Transplantation?
- Eat a balanced diet: Adequate protein, calories and essential nutrients support general hair growth.
- Avoid smoking: Tobacco and nicotine can impair circulation and wound healing.
- Handle the scalp gently: Avoid excessive pulling, heat and harsh chemical treatments.
- Manage relevant medical conditions: Scalp inflammation, thyroid disease or deficiencies may need clinical assessment.
- Use medicines as prescribed: Do not start or stop treatments based solely on perceived density.
Can Minoxidil or Finasteride Help After Hair Transplantation?
Minoxidil
Topical minoxidil may help manage certain forms of hair thinning, especially androgenetic alopecia. It can cause irritation, dryness or unwanted hair growth and is not a guarantee of improved graft survival.
Finasteride
Finasteride reduces the conversion of testosterone to dihydrotestosterone (DHT). It may help slow hereditary hair loss in selected men but can cause sexual adverse effects and mood changes. Persistent sexual symptoms and suicidal thoughts have been reported. A qualified prescriber should assess individual risks and benefits.
Is PRP Therapy Necessary for Low Density After a Transplant?
Platelet-rich plasma (PRP) therapy uses a platelet-rich preparation from the person’s blood, injected into selected scalp areas. Studies have reported possible benefits in some settings, but evidence for routine PRP to improve transplant outcomes remains limited and inconsistent. It is not required for everyone with low visible density at five months.
When Should You Seek Medical Evaluation?
Contact a healthcare professional if you experience increasing redness, severe pain, pus, fever, unusual bleeding, progressive scarring or other worsening scalp symptoms. The Cleveland Clinic’s hair transplant recovery guidance describes postoperative care and warning signs requiring prompt attention.
Arrange follow-up if there is little visible growth or if the pattern of thinning continues to worsen. Do not wait for a fixed month when signs of infection or other complications appear.
When Can Final Hair Transplant Density Be Assessed?
Hair-transplant appearance commonly continues changing during the first year, and some individuals experience further maturation after twelve months. A meaningful assessment considers coverage, shaft thickness, new growth, scalp condition and changes in natural hair loss.
Visual density is not the same as the number of grafts. Hair colour, thickness, texture, length and styling can influence how much scalp remains visible.